The air turns sharp before you notice the color of the leaves. One morning, you step onto the porch, pull your jacket tight against your collarbone, and feel it—that unmistakable autumn crispness that carries a silent warning. The seasons are shifting. And with that shift comes an invisible tide, moving quietly through office buildings, crowded subway cars, and elementary school hallways.
We talk about health policy as if it were carved into stone in some distant capital. We look at national headlines and expect a single, unified drumbeat. But health in a country stitched together by vast oceans of forests, lonely highways, and ten distinct provincial borders has never worked that way. When the autumn vaccination campaigns roll out for influenza and COVID-19, they do not arrive as an orderly wave. They arrive as ten different strategies played out across ten different boards. Don't miss our recent article on this related article.
Consider what this looks like on the ground.
Imagine Sarah, a thirty-eight-year-old mother of two living in a suburban neighborhood just outside Toronto. For Sarah, getting her family protected against the coming winter means navigating an online booking portal that feels like a high-stakes puzzle. She has to coordinate back-to-back appointments at a local pharmacy, balancing her youngest child's nap schedule with her own work deadlines. Ontario leans heavily on its pharmacy network, turning local drugstores into front-line defense posts where a pharmacist in a white coat administers both shots in a single visit, right between the aisle of cold medicine and the greeting cards. If you want more about the context here, Psychology Today provides an informative breakdown.
Now, shift the lens three thousand kilometers west, across the jagged spine of the Rocky Mountains, to a small logging community in British Columbia. Here, the landscape dictates the logistics. Public health nurses pack coolers with vials and drive down winding forestry roads to reach community centers and indigenous health stations. In British Columbia, the approach is deeply public-health-led, coordinated through an organized provincial registration system that texts you when it is your turn, aiming to capture isolated populations before the mountain passes freeze over for the season.
Drop down into the Atlantic provinces, and the rhythm changes entirely. In Nova Scotia, where generations of families have weathered nor'easters side by side, community mobilization often takes precedence over digital portals. Word travels through curling rinks, community halls, and church basements. The delivery mechanism is personal. It relies on the trusted family doctor or the nurse practitioner who has known your medical history since you were cutting teeth.
Why does this fragmentation exist? Why can't a country with universal healthcare issue a single, streamlined decree from coast to coast?
The answer lies in the architecture of Canadian federalism. Ottawa provides the funding through the Canada Health Transfer and procures the vaccines through centralized federal purchasing power, securing the doses and shipping them across provincial lines. But the actual administration—the distribution, the public messaging, the prioritization, the deployment of nurses and pharmacists—belongs entirely to the provinces and territories.
This division of labor is both a safeguard and a friction point. It is a safeguard because a cookie-cutter approach designed in an Ottawa boardroom would inevitably fail a remote mining town in northern Ontario or a sprawling agricultural county in Saskatchewan. Local authorities know their populations. They know where vaccine hesitancy runs deep, where access is hindered by geography, and where cultural outreach is necessary to build genuine trust.
Yet, it is a friction point because it breeds confusion. If you have family spread across provincial borders, you quickly realize that your sister in Alberta is facing a different rollout timeline, different eligibility rules for high-dose senior formulations, and entirely different booking platforms than your brother in Quebec.
We often forget that public health measures are fundamentally behavioral experiments. They rely entirely on human compliance, and human compliance is fragile. It is built on trust, convenience, and clarity. The moment a process becomes frustrating, the moment a citizen has to click through three different websites just to find an open time slot, compliance plummets.
This is where the invisible stakes reveal themselves.
Every autumn campaign is a race against a mutating virus. Influenza shifts its coat subtly year after year, a biological chameleon testing our immune memory. SARS-CoV-2 does the same, spinning off new lineages that slip past our previous defenses like smoke through a screen door. When provincial health ministries design their delivery strategies, they are trying to outrun evolutionary math.
If a province stumbles in its rollout—if its public communication is muddled or its appointment systems crash under opening-day traffic—the cost is measured in emergency room wait times come January. It is measured in cancelled surgeries, overworked nurses breaking down in hospital breakrooms, and elderly citizens spending winter weeks gasping for breath in crowded wards.
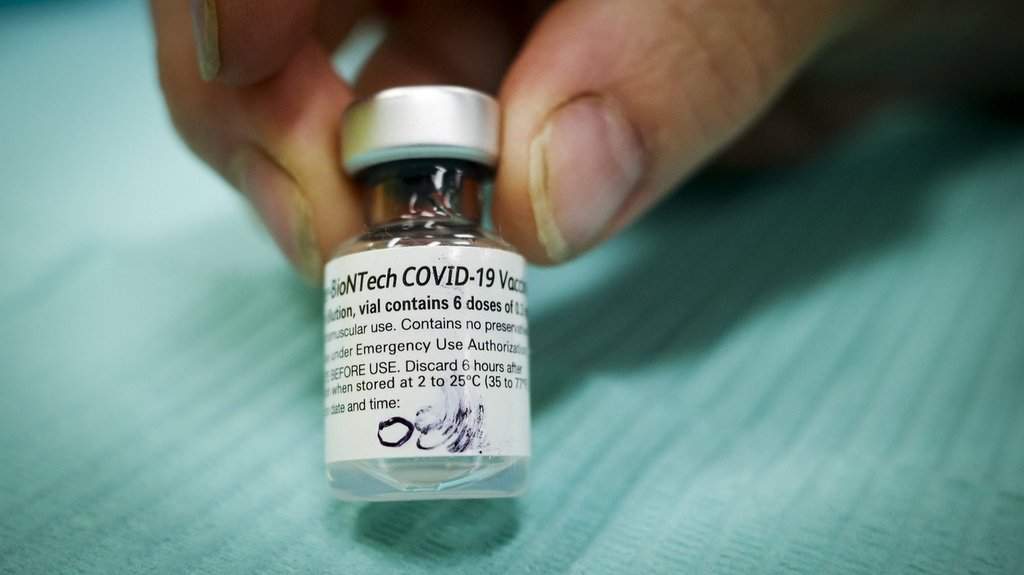
Let us be completely candid about the public mood. Fatigue is real. We are years removed from the initial shock of the pandemic, and the collective nervous system of society is frayed. When officials announce the arrival of the updated bivalent COVID boosters alongside the annual flu shot, the response is rarely enthusiastic anymore. It is often a heavy sigh.
People are tired of updates. People are tired of risk assessments. People just want normal life to feel normal again.
And that is precisely why the provincial approaches matter so much this year. The success of a campaign no longer relies on the existential fear that once drove lines around the block. It relies on seamlessness. It relies on making the right choice the easiest choice.
In places like Prince Edward Island, public health officials have leaned heavily into mobile walk-in clinics, bringing the vaccines directly to workplaces and shopping plazas. They realized that waiting for people to seek out protection was a losing battle; you have to intercept them where they already live their lives. In Manitoba, targeted outreach focuses on building bridges with newcomer communities and rural municipalities where language barriers and historical distrust have created gaps in coverage.
These are not merely logistical details. They are acts of translation. They translate cold statistical necessity—herd immunity, viral load reduction, hospitalization thresholds—into human care.
When you sit in that pharmacy chair, rolling up your sleeve while the pharmacist chats about the weather to distract you from the impending pinch, you are participating in a vast, decentralized social contract. You are not just protecting your own lungs. You are participating in a quiet, collective shield-building exercise. You are ensuring that your neighbor undergoing chemotherapy doesn't cross paths with a preventable infection at the grocery store. You are keeping the local hospital functioning when the winter freeze brings the annual spike in respiratory illness.
The map of our country is vast, rugged, and wonderfully stubborn. Our provinces will never move in lockstep. They will argue over funding, bicker over guidelines, and deploy different digital systems that occasionally fail.
But beneath that noisy surface bureaucracy lies a shared human impulse. From the salt-sprayed coasts of Newfoundland to the misty rain of Vancouver Island, health workers are unboxing vials, checking cold chains, and preparing for the long winter rush. They are doing it because they know what happens when the tide rolls in.
The needle is small. The steel is cold. But the invisible architecture holding us all together is built one quiet, ordinary choice at a time.


