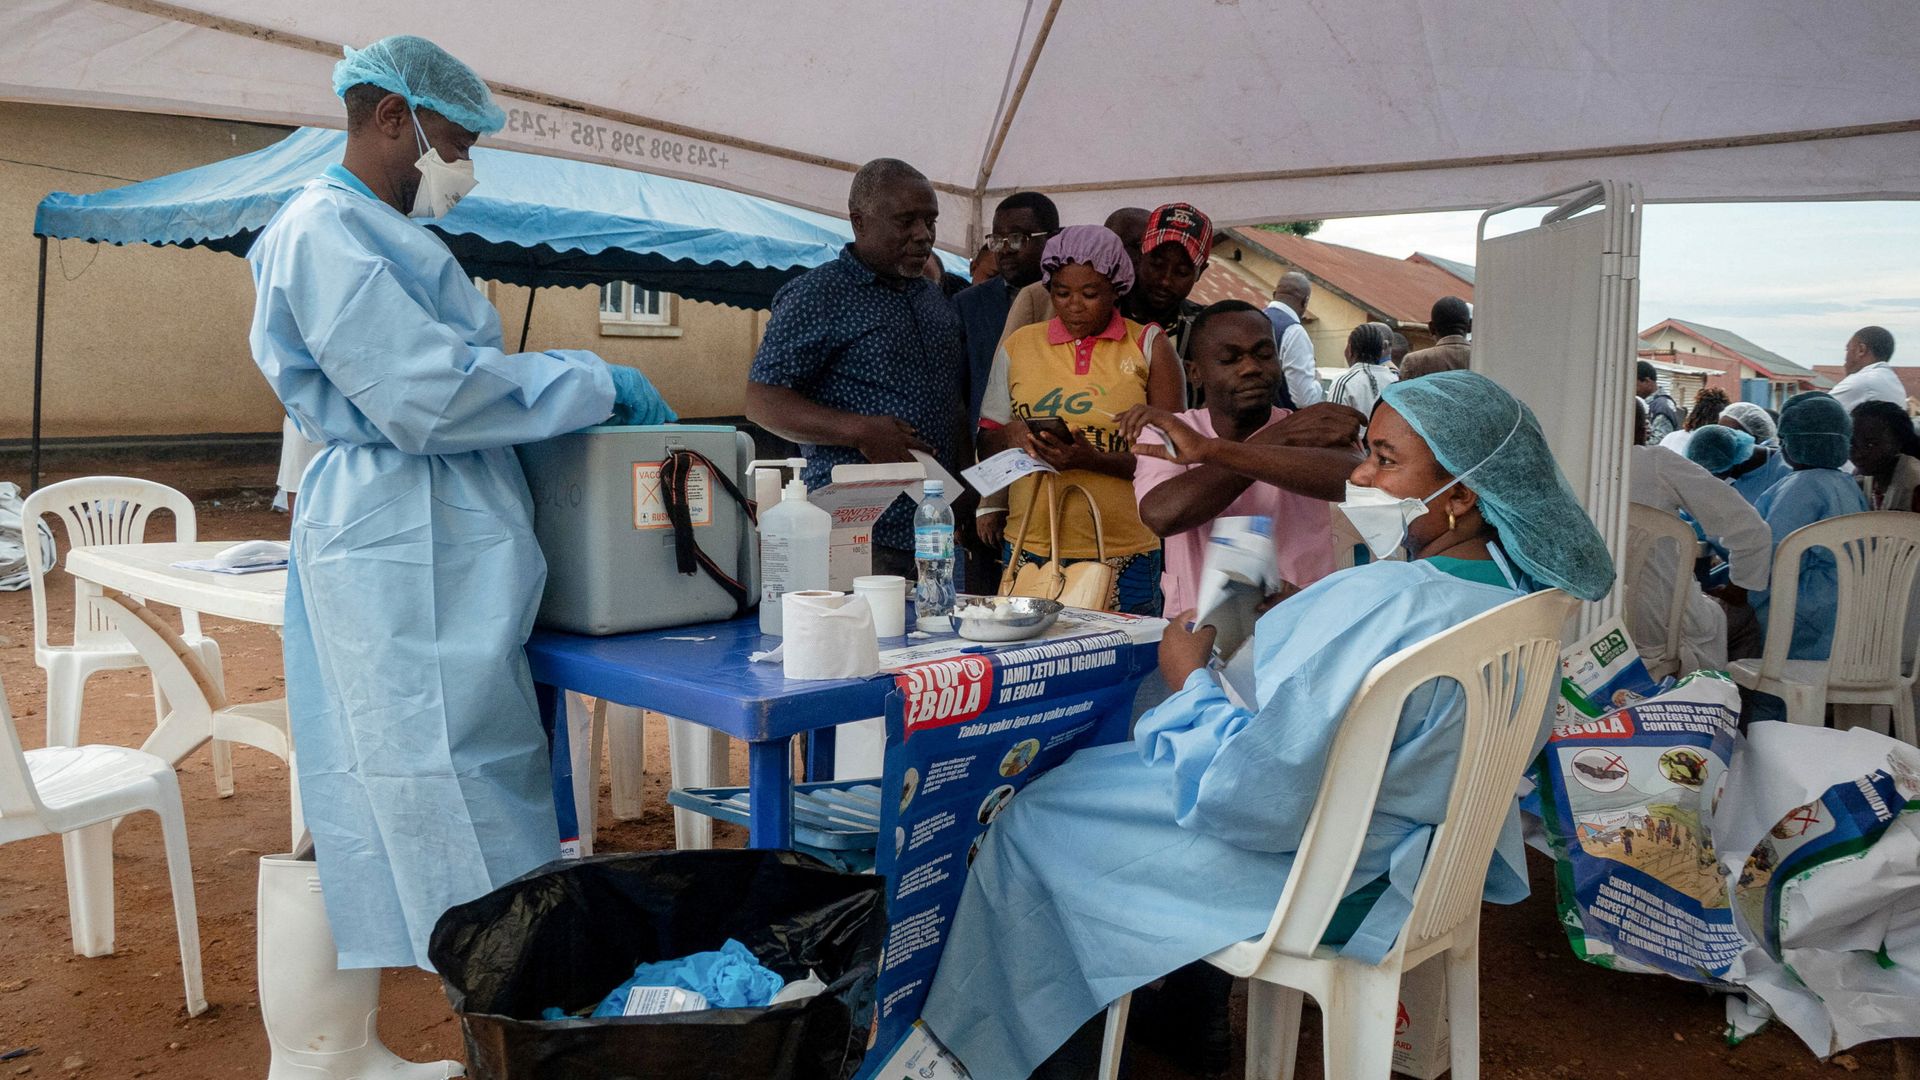
Crossing ten thousand cumulative Ebola cases in the Democratic Republic of the Congo (DRC) while a healthcare worker is killed by a machete-wielding mob exposes a coupled system failure: viral transmission expands wherever clinical containment erodes community trust, and fatal violence against responders severs the exact feedback loops required to halt spread. Standard outbreak reporting treats the cumulative case count and an isolated attack on a nurse as parallel tragedies rather than mutually reinforcing variables in a single dynamical system. Understanding how high-case-fatality filovirus outbreaks scale in conflict-affected regions—and why frontline staff face lethal hostility—requires evaluating epidemiological reproduction dynamics alongside political economy, risk communication, and operational security.
Because no full competitor article text or verified live outbreak ledger is supplied in the prompt, this analysis treats the headline—Ebola cases in the DRC surpassing 10,000 alongside the killing of a nurse treating patients by a mob armed with machetes—as a known premise to examine structural mechanisms rather than invent unverified figures. Confirmed facts include the biological properties of ebolaviruses (primarily Orthoebolavirus zairense, or Zaire ebolavirus, in historic large DRC outbreaks), the operational mechanics of case investigation and isolation, and the documented vulnerability of health workers during complex emergencies. Educated hypotheses in the sections below identify probable causal pathways linking case-count thresholds, community mistrust, and mob violence, while explicitly marking where exact field telemetry would be required to confirm local triggers. You might also find this similar story useful: What Most Coverage Misses About Congo’s Ebola Outbreak Crossing 10,000 Cases.
The Coupled Dynamics of Outbreak Scale and Frontline Violence
A cumulative case count passing 10,000 signals an epidemic that has moved far beyond localized spillover into sustained, multi-focal transmission across districts, health zones, or provinces. In epidemiological terms, each new case represents a failure to intercept a chain of transmission early enough—either because exposure occurred before symptom recognition, because symptomatic individuals avoided formal care, or because contact tracing and ring vaccination could not keep pace with movement across porous borders and active conflict corridors.
Violence against a nurse treating patients operates as a high-leverage shock to containment rather than a mere public-order incident. Frontline clinical personnel perform three interdependent functions that keep a viral hemorrhagic fever outbreak from accelerating exponentially: As extensively documented in recent coverage by Mayo Clinic, the implications are notable.
- Early Case Detection and Triage: Nurses and clinicians spot suspect cases at primary clinics and screening points, separating febrile patients before fluid exposures occur in general wards.
- Chain-of-Transmission Mapping: Trusted interactions at the point of care help identify household, burial, and clinic contacts who face the highest risk of secondary infection.
- Therapeutic Credibility: Administering supportive care, rehydration, and targeted treatments—such as monoclonal antibody therapies where available—demonstrates that treatment centers save lives rather than functioning as terminals of no return.
When a nurse is killed at or near the point of care, each of those functions degrades simultaneously. Surviving staff face acute physical risk and psychological trauma, prompting clinic closures, reduced shifts, or relocation away from high-transmission hotspots. Simultaneously, community members who already harbor doubts about external interventions interpret the violence either as confirmation of deep local grievance or as a signal that health facilities are unsafe spaces to avoid.
The feedback loop turns self-reinforcing when fear drives patients into hiding or toward informal healers. Hidden cases delay isolation, increasing household and nosocomial exposure. As secondary cases rise, external response teams often tighten perimeter controls, mandate safe and dignified burials, or deploy armed escorts. Where those measures are introduced without local legitimacy, they can intensify resentment—raising the probability of further attacks on responders and widening the transmission gap.
Why Communities Turn Hostile Toward Outbreak Responders
Mob violence involving machetes is rarely spontaneous without underlying friction; it typically emerges where acute fear intersects with pre-existing grievances, rumors, and perceived coercion. In regions experiencing protracted insecurity, displacement, economic strain, or political marginalization, residents often view outside authorities and international agencies through a lens of suspicion rather than neutral humanitarian service.
Rumor, Misinformation, and Information Asymmetry
Filovirus outbreaks are inherently terrifying because onset mimics common febrile illnesses like malaria or typhoid before deteriorating rapidly, and case fatality rates in historical Zaire ebolavirus outbreaks have frequently been high. When official explanations lag behind lived experience—or conflict with local cultural beliefs regarding illness causation and death—rumors fill the vacuum. Misinformation often claims that responders fabricate cases for funding, intentionally spread disease, or impose burial practices that violate family obligations and spiritual norms.
Perceived Coercion and Loss of Agency
Emergency public health relies on speed, which can tempt responders into top-down enforcement: rapid isolation, restricted movement, altered funeral rites, or visible security forces. When communities feel decisions are imposed on them rather than negotiated with them, protective measures can feel punitive. A clinical worker becomes a visible proxy for distant institutions, state power, or foreign intervention, concentrating diffuse anger onto an accessible target.
Economic and Opportunity Costs in Fragile Settings
Outbreak control disrupts daily survival strategies. Quarantines, market closures, travel restrictions, and loss of income hit households operating near subsistence hardest. If families perceive that response programs bring high disruption or risk without clear local benefit—such as basic primary care for non-Ebola conditions or transparent community hiring—hostility can harden quickly.
Structural Blind Spots in Conventional Outbreak Reporting
Standard news coverage and routine situation updates tend to flatten complex epidemiological and social systems into disconnected snapshots. Treating a 10,000-case milestone and a fatal attack on a nurse as separate story beats obscures four critical structural relationships.
First, cumulative totals mask spatial and temporal heterogeneity. Crossing 10,000 cases over time can reflect a slow, stubborn smolder across multiple health zones or surges driven by newly seeded clusters, even as earlier zones stabilize. Reporting the headline number without distinguishing active transmission chains from historical cumulative totals distorts where operational bottlenecks actually sit.
Second, case counts understate true community burden when care is avoided. If patients bypass treatment units out of fear or lack of access, official tallies capture those who reach formal testing or die under surveillance while missing mild, atypical, or unlinked chains. Paradoxically, a drop in reported cases immediately after an attack on a health worker may reflect collapsed reporting and surveillance rather than genuine viral decline.
Third, security incidents are frequently treated as external shocks rather than endogenous system variables. Framing mob violence purely as criminality or lawlessness misses how operational choices—such as reliance on armed escorts, opaque communication, or neglecting routine healthcare—alter threat levels on the ground. Security and public health are coupled: heavy militarization around clinics may deter immediate assault while alienating families who need care.
Fourth, clinical heroics cannot substitute for institutional trust. Individual nurses absorb extraordinary risk to keep wards running, yet personal dedication cannot overcome structural deficits in community engagement, local leadership buy-in, or sustained security governance. Expecting frontline workers to bridge deep social divides through clinical care alone places an unsustainable burden on the most exposed personnel.
Four Pillars of Outbreak Containment Under Threat
Stabilizing a high-scale outbreak when responders face lethal hostility requires rebuilding operational resilience across four interdependent pillars. None works in isolation, and weaknesses in any single pillar cap the effectiveness of the others.
1. Community Co-Governance and Risk Communication
Containment depends on shifting communities from passive recipients of instructions to active co-managers of risk. Effective programs work through established local leaders, youth groups, traditional authorities, and respected community health workers who speak local idioms and understand household dynamics. Communication must acknowledge fear directly, explain the rationale behind isolation and burial protocols without moralizing, and establish rapid two-way feedback channels to address rumors before they harden into mobilizations.
2. Integrated Primary Care and Tangential Value
Single-disease vertical responses often fail in multi-problem environments because families care about malaria, maternal health, trauma, and basic medicines every day. Integrating Ebola screening and care into broader primary health services—and ensuring non-Ebola clinical needs remain visible and supported—reduces the perception that clinics exist solely to extract patients or enforce restrictions. When facilities remain useful for everyday survival, community stakes in protecting them rise.
3. Proportionate Protection and De-Escalation Doctrine
Protecting healthcare workers requires calibrated risk management rather than blunt force. Health facilities benefit from clear physical perimeters, access controls, rapid alert systems, and contingency evacuation or shelter plans that minimize exposure without turning clinics into fortresses. Where security forces are involved, strict protocols—keeping armed personnel out of clinical wards and away from routine community outreach—help prevent routine health interactions from looking like enforcement operations.
4. Decentralized Surveillance and Adaptive Operations
When violence disrupts centralized teams or fixed treatment centers, response architectures must decentralize. Training local clinicians, supporting community-based surveillance, pre-positioning personal protective equipment and diagnostics safely, and enabling rapid shifts between mobile and fixed care allow containment to continue even when specific corridors become temporarily impassable.
Strategic Trade-Offs and Operational Limitations
No operational framework eliminates risk in an active conflict or high-tension environment, and every intervention carries trade-offs that leaders must manage transparently.
- Speed Versus Legitimacy: Rapid isolation and contact tracing curb early exponential growth, yet rushing implementation without local consultation can trigger resistance that slows containment over the medium term.
- Force Protection Versus Acceptance: Visible armed protection may deter some opportunistic attacks, but it can also reinforce narratives of coercion and make families reluctant to bring sick relatives for care.
- Centralized Control Versus Local Autonomy: Centralized coordination standardizes clinical quality and data reporting, whereas delegating authority to local teams speeds adaptation but requires rigorous training and oversight to maintain safety and infection control.
- Data Completeness Versus Safety: Pushing surveillance teams into volatile areas improves case ascertainment at the cost of staff safety; pausing high-risk outreach protects personnel while creating blind spots in epidemiological tracking.
Acknowledging these constraints prevents overpromising quick fixes. In high-friction settings, containment is rarely a straight line downward; it is an iterative negotiation between epidemiological urgency, local political reality, and physical safety.
Strategic Play for Outbreak Command
Outbreak commanders and health system leaders should immediately decouple clinical care delivery from coercive enforcement while establishing a joint health-and-community stabilization cell in every active transmission zone. Rather than responding to the killing of a nurse solely with heightened security perimeters or emergency appeals for clinical volunteers, command leadership should pause non-essential enforcement actions in the affected health zone for a defined stabilization window, convene credible local intermediaries to diagnose the specific grievances and rumors behind the attack, restore routine primary care alongside Ebola triage so facilities serve broader community needs, and deploy discreet facility-level safety and rapid-extraction protocols that protect staff without militarizing the bedside.



